
Health
PT HEALTH WATCH: Sickle cell disease persists in Nigeria despite decades of awareness


Every year on 19 June, the world marks World Sickle Cell Day to raise awareness about a condition affecting millions globally. Yet despite decades of public campaigns encouraging genotype testing and informed marriage decisions, Nigeria continues to record one of the highest burdens of sickle cell disease (SCD) in the world.
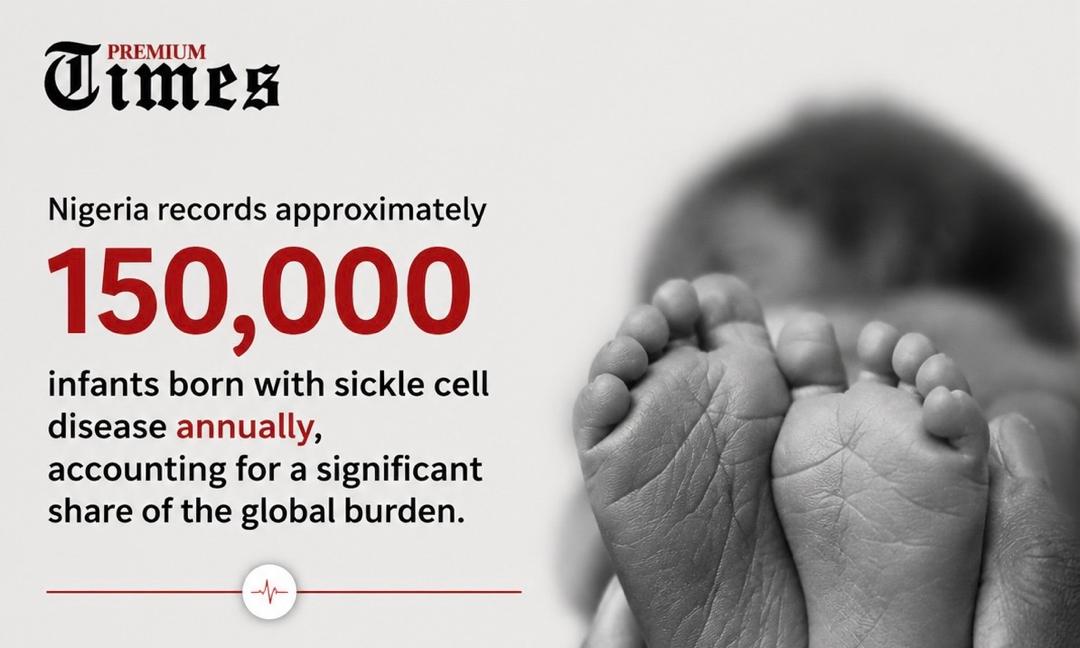
According to the Federal Ministry of Health and Social Welfare, the country records approximately 150,000 infants born with sickle cell disease annually, accounting for a significant share of the global burden.
While genotype awareness campaigns have become common in schools, churches, mosques and healthcare facilities, health experts say awareness has not translated into adequate care, early diagnosis or improved quality of life for people already living with the condition.
Speaking with PT Health Watch to mark World Sickle Cell Day, medical and maternal health experts highlighted major gaps in Nigeria’s response to the disease, including weak newborn screening, limited access to treatment, under-resourced primary healthcare and persistent misconceptions.

Beyond genotype awareness
For many Nigerians, discussions around sickle cell disease often focus on genotype compatibility and preventing new births affected by the condition.

However, Happiness Akinde, a medical doctor, said public health conversations must also prioritise the millions already living with the disease.
“Genotype awareness has been extremely important because it helps prevent new cases of sickle cell disease through informed reproductive decisions. However, there is a growing recognition that awareness efforts should also focus on people already living with the condition,” she said.
Ms Akinde explained that although education remains important, knowledge alone does not prevent sickle cell crises.
She noted that even patients who carefully follow medical advice can still experience painful episodes triggered by infections, dehydration, physical or emotional stress, poor sleep and other factors.
According to her, reducing the frequency of crises requires a combination of patient education, preventive treatment, reliable healthcare services and strong social support systems.
She added that conversations around hydration, infection prevention, medication adherence, nutrition, mental health, routine screenings and early recognition of complications deserve as much attention as genotype counselling.
The hidden cost of living with sickle cell disease
Beyond medical challenges, Ms Akinde noted that socioeconomic realities continue to worsen outcomes for many patients.
She said many families struggle to afford medications, transportation to hospitals and routine laboratory investigations required to monitor the disease.
Others live far from healthcare facilities or lack health insurance coverage, making regular care difficult.
“Effective management requires more than personal responsibility. It requires a healthcare system that supports patients consistently,” she said.
Essential medications such as folic acid, antibiotics, pain-relieving drugs and hydroxyurea, a disease-modifying therapy widely recommended for sickle cell disease remain inaccessible to many patients due to cost and availability challenges.
As a result, she noted, many people seek care only when complications become severe rather than receiving preventive treatment that could improve long-term outcomes.
Healthcare system gaps
Ms Akinde explained that weaknesses within the healthcare system continue to affect outcomes for people living with sickle cell disease.
She noted that primary healthcare workers, often the first point of contact for patients, may lack adequate training in sickle cell management, leading to delayed diagnosis of infections, poor follow-up care and inadequate pain management.
She added that some patients face delays in emergency treatment because healthcare providers underestimate the severity of sickle cell pain or are unfamiliar with recommended care protocols.
She also highlighted persistent misconceptions about the disease, including beliefs that crises result solely from poor self-care or that people living with the condition cannot live successful lives.
In addition, she said that some patients face stigma when seeking treatment because their pain is often doubted, while reliance on traditional remedies and delayed hospital visits can further worsen complications.
Poverty, gaps in prevention
Halimat Jimoh, a nurse and a professional midwife, reiterated that poverty, limited healthcare access and weaknesses within primary healthcare facilities contribute significantly to recurrent sickle cell crises.
“I have seen families who understand their child’s condition but simply cannot afford transportation to health facilities, medications, laboratory investigations or regular follow-up appointments,” she said.
Ms Jimoh believes one of Nigeria’s biggest failures is waiting until marriage discussions begin before educating people about genotype compatibility.
She argued that genotype education should begin much earlier through schools, adolescent health programmes and routine reproductive healthcare services.
She also identified major gaps during pregnancy and after delivery.
According to her, many pregnant women undergo genotype testing but receive little counselling about the implications for future pregnancies and their children.
More concerning, she said, is the absence of routine newborn screening across most health facilities.
“Too many babies leave health facilities without any form of newborn screening, meaning families only discover the child has sickle cell disease after repeated illnesses and hospital admissions,” she said.
Although babies with sickle cell disease often appear healthy at birth, Ms Jimoh explained that organ damage can begin long before obvious symptoms emerge.
As foetal haemoglobin gradually decreases during infancy, sickling becomes more pronounced, potentially affecting organs such as the spleen even before painful crises occur.
“Waiting until a child starts having repeated crises means we have already missed an important window to prevent complications and improve long-term outcomes,” she said.
Newborn screening

Globally, newborn screening is recognised as one of the most effective strategies for reducing childhood deaths associated with sickle cell disease.
Early diagnosis allows healthcare workers to monitor affected children closely, educate caregivers, prevent infections and detect complications before they become life-threatening.
Yet routine newborn screening remains largely unavailable across much of Nigeria.
According to Ms Jimoh, inadequate funding, poor infrastructure, shortages of trained personnel and weak referral systems have prevented the intervention from becoming standard practice nationwide.
What Nigeria must do
For both experts, reducing the burden of sickle cell disease will require coordinated action across the healthcare system.
Ms Jimoh identified three priority interventions which includes; strengthening genotype education and counselling before conception, implementing nationwide newborn screening programmes, and improving primary healthcare services to provide continuous follow-up care and caregiver education.
Ms Akinde on the other hand, advocated a broader approach that includes expanding newborn screening, improving access to affordable medications such as hydroxyurea, strengthening primary healthcare systems, training healthcare workers and ensuring universal access to emergency care.
READ ALSO: PT Health Watch: Hidden genotype risks beyond AA, AS drive Nigeria’s sickle cell burden- Expert
Both experts agreed that sickle cell disease must no longer be treated as a neglected condition.
Instead, they argue, it should be recognised as a major public health priority requiring sustained investment, stronger policies and improved healthcare access.
With better diagnosis, affordable treatment and consistent support, they say, people living with sickle cell disease can live longer, healthier and more productive lives.
The theme for this year’s World Sickle Cell Day, “Closing the Survival Gap: Equity in Sickle Cell Disease,” emphasises global and local action to improve support, care, and awareness for patients, while encouraging stronger advocacy for better health outcomes.







The federal government says it has disbursed N249.6 billion to the Basic Health Care Provision Fund (BHCPF) in the past three years, representing 77.1 per cent of the N323.6 billion disbursed since the fund was established in 2019.
The government also plans to expand direct financing to at least 17,600 primary healthcare facilities and provide health insurance coverage for about 90,000 Nigerians in correctional facilities.
The Minister of State for Health and Social Welfare, Iziaq Salako, disclosed this on Wednesday in Abuja during a ministerial briefing on three years of implementation of the fund under President Bola Tinubu’s administration.
Established under the National Health Act 2014, the BHCPF is designed to improve access to essential healthcare, particularly for poor and vulnerable Nigerians.
Mr Salako said the fund had become a key instrument for implementing the Nigeria Health Sector Renewal Investment Initiative, launched in December 2023 to strengthen healthcare delivery and financing.
Disbursements and allocations
According to Mr Salako, total releases to the fund stood at N422.3 billion as of September 2026, with N323.6 billion disbursed.
He said the Ministerial Oversight Committee approved an additional N40.76 billion at its meeting on 14 October. The approval is expected to raise cumulative disbursements to N364.3 billion, including N290.2 billion under the Tinubu administration, according to the statement.
Speaking on the latest allocation, Mr Salako said N19.87 billion would go to the National Health Insurance Authority, N18.34 billion to the National Primary Health Care Development Agency, N2.04 billion to emergency medical treatment and N509.48 million to the Nigeria Centre for Disease Control and Prevention.
He said the allocations would support health insurance, primary healthcare services, emergency medical response and disease surveillance.
Mr Salako added that the government was working with the National Assembly to increase the fund’s statutory allocation from one per cent to two per cent of the Consolidated Revenue Fund.
Health insurance and primary healthcare
On financial protection, Mr Salako said national health insurance enrolment increased from about 16.2 million people in 2023 to 23.06 million by the third quarter of 2026.
He said the BHCPF had supported insurance coverage for 3,182,943 vulnerable Nigerians with National Identification Numbers.
The fund, he added, had also supported free surgeries and rehabilitation for women with vesicovaginal fistula, emergency caesarean sections and other emergency obstetric and newborn care interventions for 96,068 women and babies.
Mr Salako said the oversight committee had also approved health insurance coverage for approximately 90,000 Nigerians in correctional facilities, with implementation expected to expand access to essential healthcare for inmates.
On primary healthcare delivery, he said direct facility financing currently supports 8,309 PHCs across the 36 states and the Federal Capital Territory.
He said the government planned to include a further 5,212 facilities, bringing the projected total to 13,521. However, the government’s broader target is to expand direct financing to at least 17,600 facilities.
Mr Salako added that the number of facilities attaining Level 2 readiness increased from 1,748 in 2024 to 3,202 in the third quarter of 2026.
He also said PHC attendance rose from 34.55 million in 2023 to 43.06 million by the second quarter of 2026.
Emergency services and health workers
On emergency medical services, Mr Salako said operational structures had been established in all 36 states and the FCT.
Through the Rural Emergency Service and Maternal Transport arrangements, emergency transport services had been established in 171 of the 172 local government areas covered by the Maternal and Newborn Mortality Reduction Innovation Initiative. The government plans to extend the initiative to 200 local government areas by December 2026.
He said the emergency response system had recorded 168,571 ambulance service episodes since 2023, covering obstetric emergencies, neonatal and under-five emergencies, road traffic injuries, snakebites, burns and other urgent medical conditions.
Mr Salako said 78,054 frontline health workers had been trained towards a national target of 120,000.
He also said the oversight committee approved phased salary support for 13,800 community-based health workers and skilled birth attendants. Under the arrangement, the federal government would cover eligible salary costs in full in the first year, 67 per cent in the second year and 33 per cent in the third year, before state governments assume full responsibility.
READ ALSO: FG partners US foundation to mobilise $1bn to tackle child malnutrition
He said the committee had also approved the operationalisation of MEDIPOOL, a pooled procurement mechanism intended to improve access to essential medicines and health commodities, subject to quality assurance and accountability safeguards.
Accountability and next steps
Mr Salako urged state governments to fulfil their counterpart financing obligations and ensure sustainable funding for primary healthcare services. He commended Katsina State for releasing N240.79 million to its State Health Insurance Agency to support expanded coverage.
He said the Ministry of Health and Social Welfare was strengthening financial accountability through the implementation of the updated BHCPF Guidelines 2.0 and collaboration with the Independent Corrupt Practices and Other Related Offences Commission to track the use of public funds.
He emphasised that timely reporting, transparent payments, and expenditure verification were necessary to ensure funds reached healthcare facilities and translated into services for patients.
Mr Salako said the government remained committed to increasing domestic health financing and improving access to essential healthcare, particularly for vulnerable Nigerians.
Discover more from Premium Times Nigeria
Subscribe to get the latest posts sent to your email.
The proportion of children who received the third dose of the pentavalent vaccine (Penta 3) in Kwara has increased from 34.9 per cent in 2024 to 50.4 per cent in 2025–2026.
Nusirat Elelu, the executive secretary of the Kwara State Primary Healthcare Development Agency, disclosed this in a statement made available to the News Agency of Nigeria (NAN) on Wednesday.
Ms Elelu explained that the development is contained in a recent survey report released by the Federal Ministry of Health and Social Welfare.
She described the latest survey findings as encouraging indicators of progress in child health across the state.
She added that the proportion of children aged 12 to 23 months who had received no vaccines declined from 48.1 per cent to 27.3 per cent within the period under review.
According to her, this reflects substantial progress in reaching more children with life-saving immunisation services.
The executive secretary explained that the pentavalent vaccine administered to children aged six, 10 and 14 weeks will protect them against five serious diseases, including diphtheria, tetanus and whooping cough.
“This improvement in our pentavalent vaccine coverage underscores the Kwara government’s effort at improving child health.
“It further reaffirms the importance of routine immunisation in protecting children and promoting healthy development,” she said.
Ms Elelu quoted the survey as saying stunting declined from 40.8 per cent to 35.5 per cent; wasting reduced from 6.1 per cent to 3.5 per cent, while underweight prevalence dropped from 24.5 per cent to 14.8 per cent.
She noted that these improvements represented encouraging development in efforts to promote child survival, healthy growth and overall wellbeing in Kwara.
READ ALSO: Nigeria Health Watch to host conference on scaling health innovations
“This is one of the greatest improvements in our nutrition indices recorded in Kwara in recent years,” she said.
She attributed the success to the state government’s investment in primary healthcare, particularly through support for nutrition-sensitive interventions and the biannual Maternal, Newborn, and Child Health Week.
She reiterated the agency’s commitment to strengthening primary healthcare delivery through routine and outreach immunisation, community mobilisation, nutrition services and growth monitoring.
She enjoined parents and caregivers to sustain the gains by taking their children to the nearest primary healthcare centre for free routine immunisation.
Ms Elelu advised them to keep their immunisation cards up to date, participate in community outreach programmes, and ensure regular monitoring of their children’s growth.
Discover more from Premium Times Nigeria
Subscribe to get the latest posts sent to your email.
-

 Business3 days ago
CBD COP17: Nigeria, France Push for Faster Action on 30×30 Biodiversity Target
-
News3 days ago
AI delivers ‘zero financial payoff’ to most companies, Apollo economist says
-
Health2 days ago
Ebola: ₦100,000 weekly allowance for quarantined contacts was unplanned
-
News2 days ago
Poor AI data pipelines could fuel cyber exploitation in Nigeria, regulator warns – Technology Times





