
Health
Osun’s rural PHCs:Despite billions of naira spent, challenges remain



The overgrown grasses are the first sign of neglect at Agbinpa Primary Healthcare Centre in Ede South Local Government Area of Osun State. They cover parts of the compound, brushing against walls with peeling paint and deep cracks. Sections of the facility have become unusable, while others have fallen into disrepair after years without major rehabilitation.
Next to the health centre stands a staff quarters commissioned in March 1999, a reminder of how long the facility has served the community and how little has changed over the years.
Getting to the facility was difficult. It took this reporter about an hour on a commercial motorcycle from Osogbo to Agbinpa, travelling along long stretches of uneven rural roads.
It was in late May, and Rashidat Lamidi was attending to patients. For years, she has run the health centre as its sole caregiver and administrator. Mrs Lamidi attends to pregnant women, children, and other patients, responds to emergency calls even after leaving work, clears the surroundings and, at times, buys basic consumables when they are out of stock.
“Even if I’m at home and somebody comes to call me because a child is sick or a woman wants to give birth, I will come,” she said.

Mrs Lamidi said the state government pays her salary regularly. But it does not extend the same attention to the facility, despite many politicians and government officials visiting over the years, particularly during election periods.
“They come here, but they don’t do anything.”
The impact of the deteriorating infrastructure extends beyond the building itself.

Because the facility has no functional laboratory, patients who need basic blood tests have to travel about 26 kilometres to Ede. Although a few delivery instruments were available during PREMIUM TIMES’ visit, they were inadequate for the number of patients the facility serves. Women in labour buy gloves for the nurse and buy methylated spirit and other consumables before receiving care.
As the only official, Mrs Lamidi is concerned about the health centre’s future after her retirement.
“I don’t know what will happen to this place,” she said.

Residents count the cost
The poor condition of the PHC has not diminished its importance for the residents of Agbinpa. It has only made healthcare harder to access and more expensive.
Iya Beji, a woman who gave birth to each of her five children at the facility, praised the commitment of the lone nurse.
“The nurse is good. It is only because of the condition of the hospital that people do not come here,” she said.
According to the woman, patients who need scans are referred to Ede, where transport alone costs about N6,000.
“If someone is sick, what can we do? We have to go.”

Abdulrahaman Babatunde, another resident, said commercial motorcycles rarely use the route because of its condition.
“If you hire a bike, it can cost N6,000,” he said. “If the rider waits for you, they charge as much as N10,000.”
Mr Babatunde said farmers also suffer when taking produce to nearby markets, limiting economic activity in the community.

Electricity is another challenge for the locals. Private operators of solar charging points charge between N400 and N700 to charge their phones or power banks.
“There has been no light here for a long time,” Mr Babatunde said. “The poles and wires are still there, but there is no electricity.”

Another community, another barrier
About an hour’s ride from Osogbo, Abudo PHC in Egbedore LGA presents a different, but equally troubling picture.
Here, the biggest obstacle to healthcare begins long before patients reach the facility.
The road to the community is so bad that commercial motorcyclists avoid it. When this reporter arrived around 1 p.m., the facility was locked.
Through dusty louvre windows, patient registers and other documents could be seen scattered across the rooms. Cobwebs hung from parts of the building, suggesting some sections had remained unused for some time.

No health worker was on the premises. Instead, telephone numbers had been written on a wall for anyone who needed them to call.
This reporter dialled the numbers repeatedly, but the calls either failed to connect or the phones were switched off.
Chief Alao, a community leader, said Abudo’s PHC serves the community as well as several neighbouring settlements.
He said years of poor road infrastructure have isolated the area, affecting access to healthcare and residents’ livelihoods.

“This road was not constructed by the government,” he said. “The community did it ourselves, although there are still many potholes.”
Kemi Olawole, a palm kernel processor, said the facility refers patients whom they cannot manage to a health facility in Ede, about 16km from Abudo.
Ms Olawole added that residents now depend on a vendor who transports orthodox medicines into the community on a motorcycle because there is no pharmacy in Abudo.
Without him, she said, many residents would have to travel outside the community to buy essential medicines.
For another resident, Kehinde Olumide, who also works in the palm kernel oil trade, transportation remains one of the community’s biggest challenges.
“We hardly see motorcycles here,” he said. “And when you get one, it is very expensive because of the road.”
A renovated facility, familiar problems
About 36 kilometres away, in Ekusa, Odo-Otin LGA, residents said the community’s PHC was renovated in 2020.
An inscription on the building states that the project was carried out by the Odo-Otin Local Government and commissioned on 15 March 2020.
But six years later, many of the problems affecting healthcare delivery remain in the community.
When PREMIUM TIMES visited the facility, parts of the premises were overgrown with weeds. The hospital’s borehole was not functioning.

Unlike Agbinpa, where the lone nurse openly discussed the facility’s challenges, health workers in Ekusa declined to speak. One who requested anonymity said they were not permitted to comment on issues relating to PHCs.
“Many people have come here asking questions,” she said. “If it is something I cannot talk about, it is better I don’t say anything. During our meetings, we are always told that if anyone asks questions about PHC, we should refer them to the appropriate authorities.”
She directed this reporter to the Osun State Primary Health Care Development Agency, explaining that decisions regarding the facility were handled centrally.
Residents later explained that health workers’ reluctance to speak was not unusual. According to them, the facility typically closes around 4 p.m. Patients who arrive later have to wait until the next day or travel to another community for treatment.
A woman who identified herself as Mojisola said residents seek treatment elsewhere whenever the facility cannot meet their medical needs.
Abdulrahaman Wasiu, a spiritual and youth leader in the community, said nothing had changed since the 2020 renovation.
“People only came to paint the building,” he said. “Apart from that, nothing much changed.”
Pointing to his hand, which he said had once suffered a dislocation, Mr Wasiu recalled visiting the health centre for treatment but leaving without receiving the care he needed.
According to him, the facility has existed for as long as he could remember, but has remained chronically understaffed.

When Mr Wasiu accompanied this reporter back to the facility, they met another man wearing an “Imole cap” who identified himself as a supporter of Governor Ademola Adeleke. He confirmed the health workers’ gag and that enquiries should be directed to the Osun State PHCDB.
While acknowledging that the facility required attention, he said Governor Adeleke would intervene if he became aware of its condition.
Following the money
The problems observed during PREMIUM TIMES’ visits suggest that, despite years of government investment and prior reporting highlighting similar concerns, many of the challenges facing health facilities remain unresolved.
The conditions at Agbinpa PHC stand in sharp contrast to the Osun State government’s growing financial commitment to healthcare.
Between 2020 and 2026, the state budgeted about N157.74 billion for the health sector, according to an analysis of approved budget documents by PREMIUM TIMES.
In 2020, the state approved N7.2 billion for health, representing 6.02 per cent of the N119.55 billion budget. The allocation rose to N9.8 billion (8.93 per cent) in 2021 and N12.4 billion (9.56 per cent) in 2022.
Health spending reached N17.92 billion, representing 12.96 per cent of the state’s N138.27 billion budget in 2023, the highest proportion recorded during the review period.
Although the percentage later declined, the nominal value of health allocations continued to increase. The state budgeted N18.6 billion for health in 2024, N32.58 billion in 2025 and N59.24 billion in the approved 2026 budget.
Budget implementation data reviewed by PREMIUM TIMES also points in the same direction.
According to BudgIT’s State of States reports, Osun’s capital expenditure rose from N18.7 billion in 2020 to N118.4 billion in 2024. The reports also show that actual health expenditure increased from N10.6 billion to N17.7 billion over the same period, while the Ministry of Health and Human Services recorded improved performance ratings.
On paper, the figures indicate an increase in public investment in healthcare. The question, however, is how those investments have translated into community-level services.
To answer that, PREMIUM TIMES examined procurement records published by the state government.
Procurement records
The records show that between 2020 and 2024, the Ministry of Health awarded contracts worth hundreds of millions of naira for the renovation of health facilities, the procurement of medical equipment, the installation of solar power systems, the repair of boreholes, and other primary healthcare projects.
In 2020, the ministry awarded a N35.7 million contract to Olupopson Nigeria Limited for the rehabilitation and upgrading of General Hospital, Ifetedo. It also approved N6.8 million for the procurement of 4,000 cartons of noodles, with both projects listed as completed on the state’s procurement portal.
The following years saw continued spending on medical equipment, including theatre lamps and diathermy machines, X-ray machines, instrument trolleys, suction machines, emergency stretchers, ultrasound scanners, ECG machines, hepatitis B testing kits, HIV/AIDS consumables, laboratory supplies, computer systems, and other surgical equipment.
Most of the contracts reviewed by PREMIUM TIMES were marked as completed, while a few remained active or had no completion status.
The largest investments reviewed during this investigation were recorded in 2024.
Procurement records show that the state awarded multiple contracts valued at between N426 million and N592 million for the renovation of PHCs across the state’s three senatorial districts.
Separate contracts worth more than N188 million each were also awarded for the supply and installation of solar power and inverter systems across the three districts, while additional contracts ranging from N119 million to N556 million were approved for the sinking and repair of boreholes.
At the time PREMIUM TIMES reviewed the records, many of the 2024 projects were still listed as “Active” on the state’s procurement portal.
However, the procurement documents do not identify the individual PHCs covered under the various phases of the projects.
As a result, PREMIUM TIMES could not independently verify whether Agbinpa PHC in Ede South, Abudo PHC in Egbedore or Ekusa PHC in Odo-Otin were among the facilities selected for renovation, solar installations or borehole projects.
Statements by government
Throughout the period covered by this investigation, the state government maintained that strengthening primary healthcare remains one of its priorities.
During an inspection of renovated PHCs in Telemu, Ola-Oluwa LGA, and Ido-Osun, Egbedore LGA, in March 2025, Governor Adeleke said his administration was committed to improving access to healthcare, particularly for residents of rural communities.

According to the governor, the state embarked on the rehabilitation and upgrading of PHCs to strengthen healthcare delivery at the grassroots level.
“I am glad that our people are now benefiting from the outcome of the upgrade and renovation of the health centres. I assure Osun people that we will not relent on the upgrade of our health facilities,” Mr Adeleke said.
He added that the government was prioritising improvements at the primary healthcare level before extending interventions to secondary and tertiary facilities, arguing that stronger primary healthcare would enable earlier detection and treatment of illnesses.
In his third anniversary broadcast in November 2025, the governor also said his administration had rehabilitated more than 200 PHCs across the state.
According to him, the projects included structural rehabilitation, clean water systems, perimeter fencing, roofing repairs, furniture, sanitation facilities, and solar power. He added that another phase covering nearly 200 additional facilities was already underway.
The governor also highlighted the revitalisation of the Osun Health Insurance Scheme, expanded insurance coverage, free surgical interventions across the state’s nine federal constituencies and a $500,000 performance award for the state’s progress on universal health coverage indicators.
Yet, in the three communities visited, this reporter found deteriorating health infrastructure, limited services, staffing shortages and difficult access to healthcare, suggesting that, for some rural communities, the benefits of the state’s healthcare investments remain difficult to see.
Government cites funding constraints, ongoing reforms
PREMIUM TIMES contacted the Osun State Primary Health Care Development Agency on the findings.
In a telephone interview, the agency’s Executive Secretary, Adesina Igbalaye, repeated that the state had invested significantly in primary healthcare.
He said the agency conducts routine monthly and quarterly assessments of health facilities to monitor infrastructure, staffing, equipment, and service delivery, with the reports used to identify facilities requiring intervention.
According to him, the government adopted a strategy of upgrading one focal PHC in each ward.
The selected facilities, he said, received renovations, solar power systems, boreholes, medical equipment and other improvements intended to strengthen healthcare delivery.
Mr Igbalaye also said the government introduced stipends for volunteer health workers who had previously served without pay and provided counterpart funding for health programmes implemented with development partners.
Responding to PREMIUM TIMES’ findings that the facilities visited lacked basic services, he said the ongoing revitalisation programme was designed to prioritise one focal facility in each ward while other centres continued to provide routine services.
He attributed delays in extending improvements to all facilities to funding constraints.
According to him, implementation of parts of the programme slowed after disputes over local government administration affected access to local government funds beginning in February last year.
He said the funding challenge affected the pace of ongoing projects, although work has continued in some facilities through other government interventions, including drug supply and routine support for primary healthcare services.
Mr Igbalaye added that the agency’s assessments have enabled it to identify infrastructure and service gaps across facilities, insisting that the government remains committed to improving access to primary healthcare across the state.
Agency report echoes field findings
PREMIUM TIMES requested records of the PHCs revitalised under the state’s programme, the criteria used to select focal facilities and the agency’s most recent assessment reports.
Mr Igbalaye provided a copy of the board’s “5-Day Routine Quarterly Quantitative Integrated Supportive Supervision at PHCs in 15 Selected LGAs” report for the second quarter of 2026.
The report, prepared by the board’s Directorate of Planning, Research and Statistics, said supervision teams visited at least 150 PHC facilities across 15 selected LGAs between 1 and 5 June 2026.
The exercise assessed health facility infrastructure, staffing, service delivery, medicine availability, immunisation performance, maternal and child health indicators, and data quality.
However, the report did not identify the 15 LGAs assessed or list the facilities visited.
It also did not provide facility-level findings, making it impossible to independently determine whether Agbinpa, Abudo and Ekusa were among the facilities assessed or how each performed during the exercise.
Even so, the report acknowledged many of the challenges residents described during this investigation.
It identified shortages of health workers, stock-outs of essential medicines and consumables, absenteeism among some health workers, poor record-keeping, and difficult road conditions that affect access to some rural facilities.
The report stated that stock-outs of malaria medicines were recorded at 50 facilities, while 20 facilities lacked oral rehydration salts (ORS), a basic treatment for managing diarrhoea.
It also noted that difficult road conditions during the rainy season affected access to some rural PHCs, while shortages of human resources remained a challenge across the system.
Among its recommendations, the board called for the procurement of essential medicines and consumables, the conversion of ad hoc and volunteer health workers to permanent staff, improved monitoring of staff attendance, and increased funding for supervision activities.
‘Buildings alone do not make PHCs functional’
The conditions documented by PREMIUM TIMES point to broader weaknesses in Nigeria’s primary healthcare system, where investments in infrastructure do not always translate into accessible, quality healthcare, according to Sheriff Gbadamosi, Advocacy and Community Engagement Manager at Nigeria Health Watch.
Mr Gbadamosi said PHC is meant to be the first point of contact with the health system. When residents travel long distances for services that should be available in their communities, he said, it raises questions about whether public investments are delivering the intended results.
“Access should not be measured by the presence of a building alone,” he said. “It should be measured by whether facilities are adequately staffed, stocked with essential medicines and equipped to provide basic services.”
He noted that while renovating health facilities is important, infrastructure alone cannot improve health outcomes.
According to him, the experiences documented in Agbinpa, Abudo and Ekusa reflect wider challenges facing Nigeria’s PHCs system, including workforce shortages, weak supply chains, financing gaps and governance issues.
Mr Gbadamosi also expressed concern about the burden placed on lone health workers, citing the case of the nurse at Agbinpa PHC, who attends deliveries, responds to emergencies outside working hours and sometimes buys basic consumables for patients.
“No PHC should depend entirely on the extraordinary commitment of one individual. Strong health systems are designed so that quality care does not rely on heroism,” he said.
He added that facilities enrolled under the Basic Health Care Provision Fund (BHCPF) are expected to receive quarterly funding to improve infrastructure, reduce medicine shortages and support additional health workers.
The expert also linked the findings to Nigeria’s high out-of-pocket healthcare spending, noting that transportation costs, referrals and the purchase of medicines and consumables impose additional financial burdens on households and often delay treatment.
Commenting on the Osun State Government’s strategy of prioritising selected “focal” PHCs, Mr Gbadamosi said concentrating resources on designated facilities may be necessary where funding is limited, but warned that surrounding communities should not be left without access to essential healthcare.
He said the success of any revitalisation programme should be measured not by the number of renovated facilities but by whether residents have better access to timely, affordable, high-quality healthcare.
This reporting was supported by the Centre for Journalism Innovation and Development (CJID).
Discover more from Premium Times Nigeria
Subscribe to get the latest posts sent to your email.




Health
SPECIAL REPORT: In Kaduna, a new intervention is saving women from excessive bleeding after childbirth

At a primary healthcare centre in Kaduna State, Zainab Garba remembers what health workers used to do when a woman began bleeding heavily after childbirth.
They would provide initial care, explain the seriousness of the situation to her relatives and prepare her for referral to a higher-level health facility.
For Ms Garba, an antenatal care provider at PHC Abdukwari in Sabon Gari LGA, who also assists with deliveries, there were limits to what health workers at her level could do.
But she said that began to change after she was trained to use the E-MOTIVE approach to detect and manage postpartum haemorrhage (PPH).
“With the presence of E-MOTIVE and the training given to us, we now do better,” she said. “The majority stop bleeding without even being referred.”

Ms Garba is one of the frontline health workers met during visits to primary healthcare facilities in Kaduna, where an intervention is attempting to address a longstanding challenge in maternal healthcare: shortages of skilled health workers to manage potentially life-threatening complications at the primary healthcare level.
The intervention, known as the Task Shifting Task Sharing (TSTS) project, is implemented by Pathfinder International in partnership with Impact Catalysts, with support from the Gates Foundation. It is designed to strengthen the capacity of Community Health Extension Workers (CHEWs) to take on specific maternal healthcare responsibilities at the primary healthcare level.
Under the project, 77 CHEWs have been trained across 77 primary healthcare facilities in nine LGAs: Kaduna North, Kaduna South, Igabi, Soba, Sabon Gari, Makarfi, Kaura, Jema’a and Zangon Kataf.
They are supported by nine clinical mentors, one in each LGA, and nine Reproductive Health Coordinators.
Programme records reviewed by PREMIUM TIMES show that the CHEWs received competency-based training in PPH prevention and management, basic emergency obstetric and newborn care and other maternal and newborn health services.
A key component of the training focuses on preventing, detecting, and managing PPH using the E-MOTIVE approach.
The deadly toll of PPH
PPH, or excessive bleeding after childbirth, is one of the leading causes of maternal deaths worldwide.
It can occur within the first 24 hours after childbirth, known as primary PPH, or between 24 hours and six weeks after delivery, known as secondary PPH.
A 2026 Lancet Series highlighted by the World Health Organisation estimates that PPH affects about 27 million women and kills nearly 43,000 women globally each year. It also indicates that PPH costs countries, health systems and families globally over $10 billion each year.
The burden is particularly high in poorer regions, with the WHO estimating that more than 85 per cent of deaths from PPH occur in sub-Saharan Africa and South Asia.
In Nigeria, PPH remains a major contributor to maternal mortality, accounting for an estimated 23 to 30 per cent of maternal deaths, according to WHO.
Recent surveillance data from Kaduna also show the continuing toll of PPH. A Kaduna State Primary Health Care Board review for the first quarter of 2026 identified PPH as the leading cause of maternal death among cases for which causes were detailed, with PPH-related deaths reported in Kudan, Birnin Gwari and Lere LGAs.
The finding followed a similar pattern in the last quarter of 2025, when the state’s community maternal and perinatal death surveillance report linked maternal deaths in several LGAs to PPH, often following deliveries outside health facilities.
In many cases, according to the WHO, there are no identifiable risk factors, making early detection and rapid treatment particularly important.
Lewis Aituma, a senior resident doctor in Obstetrics and Gynaecology, described PPH as “the obstetrician’s nightmare,” particularly in countries such as Nigeria, where access to emergency obstetric care remains inadequate.
He said women with multiple pregnancies, prolonged labour, fibroids, anaemia or previous Caesarean deliveries may face a higher risk.
If severe bleeding is not controlled quickly, he added, a woman can develop shock, organ failure and die.
A race against bleeding
Recognising excessive blood loss early and starting treatment quickly is therefore critical to preventing severe complications.
Under its latest guidance, WHO recommends objective measurement of blood loss after childbirth. Although PPH has traditionally been diagnosed when a woman loses at least 500 millilitres of blood after delivery, the latest guidance recommends earlier intervention when blood loss reaches 300 millilitres and is accompanied by abnormal vital signs.

One tool for doing this is a calibrated drape placed beneath the woman after delivery. It collects and measures blood, reducing reliance on visual estimation.
Once PPH is diagnosed, WHO recommends rapid use of the MOTIVE treatment bundle: massage of the uterus, oxytocic medicines to stimulate contractions, tranexamic acid to reduce bleeding, intravenous fluids, examination of the vaginal and genital tract, and escalation of care where necessary.
Together with early detection, the approach is commonly referred to as E-MOTIVE.
Evidence suggests it can make a substantial difference.
A large randomised trial involving more than 200,000 women in hospitals in Nigeria, Kenya, South Africa and Tanzania found that early detection and bundled treatment reduced, by about 60 per cent, the risk of a combined outcome of severe PPH, surgery for bleeding or death from bleeding compared with usual care.
But in Kaduna, having an effective approach is only part of the equation.
There must also be someone with the skills to use it when a woman starts bleeding.
Closing a workforce gap
Tanimu Argungu, Pathfinder International’s Kaduna State team lead, said the organisation found that many PHCs relied heavily on community-level health workers amid shortages of nurses, midwives and other highly skilled health personnel.
Programme data reviewed by PREMIUM TIMES show that CHEWs account for 28 per cent of Kaduna’s PHC workforce, while Junior CHEWs account for another 14 per cent. Together, they make up more than 40 per cent of the workforce at that level.
The data show that task shifting was already widespread before the intervention. At baseline, more than 84 per cent of the supported PHCs were already assigning some responsibilities to CHEWs and other cadres, but only 40 per cent of the staff performing those tasks had been trained to do them.
Mr Argungu said the TSTS intervention was designed to address this gap by training health workers to safely take on specific responsibilities.
“We first supported the state to adopt the policy and see how to implement it properly. We realised that many of the PHCs in Kaduna State were manned by CHEWs and JCHEWs,” he said.
He said facilities were selected partly based on maternal deaths previously reported through the state’s surveillance system, with CHEWs working in those facilities then selected for training.

Under the TSTS project in Kaduna, 77 CHEWs underwent an initial 9-day competency-based training before returning to their facilities, where clinical mentors continued to coach and mentor them.
Programme records reviewed by PREMIUM TIMES show that the mentorship component ran from October 2025 to August 2026, with nine clinical mentors conducting monthly facility-based coaching alongside LGA Reproductive Health (RH) coordinators.
After training, the CHEWs shared what they had learnt with colleagues who had not attended the initial sessions.
For Mr Argungu, the continued mentorship is critical.
“The mentorship session is key to any capacity building,” he said.
He said experience from previous training programmes showed that knowledge acquired during classroom sessions could decline after workers returned to their facilities without adequate follow-up.
He said some workers who did not attend the initial classroom training but participated in the cascade sessions and subsequent facility mentorship also showed improvement.
Adetoun Akor Aliu, Safe Motherhood coordinator at the Kaduna State Primary Health Care Board (KSPHCB), said shortages of nurses and midwives had already led PHCs to rely on CHEWs to provide some services.
Mrs Akor Aliu said the movement of health workers to federal institutions and outside Nigeria in search of better opportunities had contributed to workforce shortages.
“So task shifting, task sharing was already happening in Kaduna State,” she said.
What the Pathfinder-supported intervention did, Mrs Akor Aliu explained, was to make the practice more structured by concentrating on what CHEWs could be trained and permitted to do at the facility level.
A new approach to detecting PPH
At PHC Abdukwari in Sabon Gari LGA, Aisha Labaran, a CHEW, demonstrated how the training has changed the response to bleeding after delivery.
“Before, when we had a PPH case, we used to refer,” she said. “But now, if we have, we treat them through the E-MOTIVE procedure.”
One important change is how workers determine the amount of blood a woman has lost.
Before the intervention, visual estimation could play a major role. Now, Ms Labaran said, workers use a calibrated drape to collect and measure blood after childbirth.
WHO recommends objective measurement of blood loss because visual estimation can delay recognition of dangerous bleeding.

Ms Labaran said health workers monitor women after delivery and begin the PPH response once the diagnostic criteria are met.
She estimated that the facility had managed about 10 PPH cases since she received the training.
She said the knowledge was also spreading beyond the initially trained worker, with other technical staff benefiting from training and mentorship at the facility.
Rabiu Abdullahi, the officer-in-charge of PHC Abdukwari, said the facility previously relied on referrals for women who developed PPH because workers lacked the skills to manage the condition.
Mrs Abdullahi said the facility recorded five PPH cases in the two years preceding the intervention, all of which were referred for higher-level care.
She said three cases were referred to TundunWada Teaching Hospital, while two were referred to Major Ibrahim Abdullahi Memorial General Hospital.
She said the facility now begins managing PPH cases when they occur, rather than automatically referring every case.
“We usually referred patients with PPH to a secondary facility because we did not have the competence and skills to handle it,” she said.

Mrs Abdullahi said the training has strengthened the facility’s ability to monitor women in labour, recognise danger signs and begin managing PPH when it occurs.
She said the knowledge has also been passed on to other CHEWs at the facility, with five health workers trained.
Aisha Sambo, the Reproductive Health coordinator for Sabon Gari LGA, said nine health workers had been trained under the programme in the LGA.
Mrs Sambo monitors maternal health services across health facilities in the LGA.
She said facilities that previously relied heavily on referrals for PPH were increasingly managing cases at the PHC level following training and mentorship under the TSTS project.
What changed at Mando PHC
At Mando PHC in Afaka Ward, Igabi LGA, Hadiza Abdullahi described a change in practice.
The community health worker said some equipment and medicines used in responding to obstetric emergencies were either unfamiliar to her or not routinely used before her training.
For instance, she said she previously relied on visual estimation to judge blood loss and had never used a calibrated drape.
She also said she did not know how to use tranexamic acid for PPH or properly apply a non-pneumatic anti-shock garment, which can help stabilise a woman suffering severe blood loss while treatment or referral is arranged.
“Before, if the woman is bleeding, we can only give her misoprostol and oxytocin and refer her,” Ms Abdullahi said.
Ms Abdullahi said the facility handled several PPH cases before the intervention and referred them for higher-level care, although she could not provide records showing the exact number.

Now, she said, workers follow a more structured response, allowing them to begin managing the bleeding while determining whether the woman needs higher-level care.
Ms Abdullahi said the facility has managed about 20 PPH cases since the intervention began.
She said preparation has also changed. Rather than waiting until a complication develops, Ms Abdullahi said workers prepare emergency materials before a delivery so they can respond more quickly if something goes wrong.
Ms Abdullahi was the only worker from her facility who attended the initial training, but she said she subsequently shared what she learned with about 20 colleagues.
One of those colleagues was Hajara Yunusa, a CHEW at Mando PHC, who said she learnt the E-MOTIVE approach from Ms Abdullahi after the initial training.
Ms Yunusa said the sessions improved her understanding of how to recognise and manage PPH and also strengthened her skills in conducting deliveries.
“I learnt E-MOTIVE from Hadiza Abdullahi. I now know how to manage a woman with PPH at the PHC,” she said. “There were a lot of things I didn’t know about conducting deliveries before, which I now know after the training.”
Kyauta Isiaka, a public health midwife and TSTS clinical mentor covering Mando PHC and eight other facilities in Igabi LGA, said mentorship allows workers who did not attend the initial training to participate in practical sessions at the facility.
During her visits, she observes workers, identifies gaps and reinforces skills.
She said health workers also contact her when they encounter difficulties outside scheduled mentorship visits.

Mrs Isiaka said there was still a need for more health workers to receive comprehensive training rather than relying solely on knowledge passed down by colleagues.
“There is a need for some of the health workers to still have the complete training if possible,” she said.
What the records show
Beyond the accounts of individual health workers, programme monitoring records reviewed by PREMIUM TIMES provide some indication of what has happened across the supported facilities.
Between October 2025 and June 2026, mentored CHEWs attended 4,337 deliveries across the supported PHCs, according to the records.
During the same period, the programme recorded 192 PPH cases managed at the PHC level, 3,323 postpartum family planning insertions and 9,085 postnatal care services across the supported facilities.

The records state that some PHCs now manage PPH cases that would previously have been referred, while workers have also been trained to stabilise complications before referral when higher-level care is required.
Fatima Ma’azu, programme officer for the TSTS project, said the training had strengthened the ability of CHEWs to respond to PPH at the facility level and reduced the need for referrals.
“So far, so good, we have recorded zero maternal mortality as a result of PPH, and we have reduced referrals because the CHEWs are able to prevent and manage PPH where it happens,” she said.
More women coming to health centres
The intervention also depends on something that training alone cannot solve: women must reach health facilities before workers can help them.
The importance of reaching a health facility is also reflected in the state’s mortality surveillance. Kaduna’s Q1 2026 review found that all the maternal deaths for which the circumstances were explicitly detailed followed home deliveries involving unskilled providers.
Mrs Isiaka, the public health midwife, said community volunteers and Ward Development Committees are being used to encourage pregnant women to attend antenatal care and deliver at health facilities.
She said community structures refer women and promote facility delivery during meetings and household engagement.
Abdu Zaria, chairman of the Ward Development Committee in Afaka Ward, Igabi LGA, said the committee works with community and religious leaders to encourage pregnant women to seek care at the PHC rather than remain at home during pregnancy and childbirth.
Mr Zaria said residents had also noticed changes since more women began using the facility. He said reports of women dying during pregnancy had become rare in the community.
Mr Argungu, Pathfinder International’s Kaduna State team lead, said distrust of facilities was one of the early challenges encountered by the project, particularly where communities knew that skilled personnel were limited.
He said community engagement accompanied the health worker training to rebuild confidence in the facilities.
Sustainability efforts
The TSTS intervention was designed as a two-year project. Mr Argungu said it subsequently received a no-cost extension into early 2027, while attention increasingly shifted towards state ownership.
Programme documents reviewed by PREMIUM TIMES show that Kaduna has developed a N619.675 million Costed Implementation Plan covering 2025 to 2027.
The documents state that the plan was formally adopted by the Kaduna State Ministry of Health and the State Primary Health Care Board.
The plan covers regulatory support, quality of care, sustainability, clinical care organisation and monitoring and evaluation.
But the state says its plans for task shifting extend beyond the Pathfinder-supported project.
Mrs Akor Aliu said the state does not expect the training and mentorship of CHEWs to stop when Pathfinder’s support ends.
The reason, she said, is straightforward: “CHEWs remain more widely available across many PHCs than nurses and midwives.”

Mrs Akor Aliu said the state government has continued training frontline health workers in maternal and newborn healthcare, with further training planned.
She said more than 527 CHEWs have been trained on PPH and the E-MOTIVE approach across the state, while about 283 CHEWs have received training in essential newborn care, including newborn resuscitation.
“And presently, we have a training coming up soon strictly for 50 CHEWs,” she said.
Mrs Akor Aliu said mentorship is also continuing, with supervisors returning to facilities to assess how health workers are applying their skills and provide hands-on support where gaps remain.
Facility champions are also being selected to reinforce those skills between mentorship visits, she said.
“Continuous mentorship continues,” Mrs Akor Aliu said. “We go back, we see how they are doing, and then facility champions are being selected to continue that process.”
Programme records reviewed by PREMIUM TIMES provide some evidence of the transition, showing that the State Primary Health Care Board extended the TSTS mentorship approach to 14 LGAs in May and June 2026 without partner funding.
The transition plan also envisages reproductive health coordinators continuing monthly mentoring and incorporating TSTS quality-of-care tools into the state’s existing supervision system.
The documents further propose a dedicated budget line in the state’s 2027 Annual Operational Plan for mentorship, data reviews and related activities.
But financing remains a potential obstacle.
Mrs Akor Aliu acknowledged that state funding for health activities is not always released when required.
“Most times, the state funding is not released quickly, timely, because of cash-backing issues with the state government,” she said.
She said support from other organisations working in maternal and newborn health has helped the state continue training and mentorship activities.
Mr Argungu also identified financing as one of the challenges to expanding the intervention, saying the state may have to expand gradually if it cannot immediately fund implementation across all LGAs.
For Mrs Isiaka, sustaining the approach will require continued investment in both training and follow-up.
“We want the training to continue, and we also want the mentoring to continue,” she said.
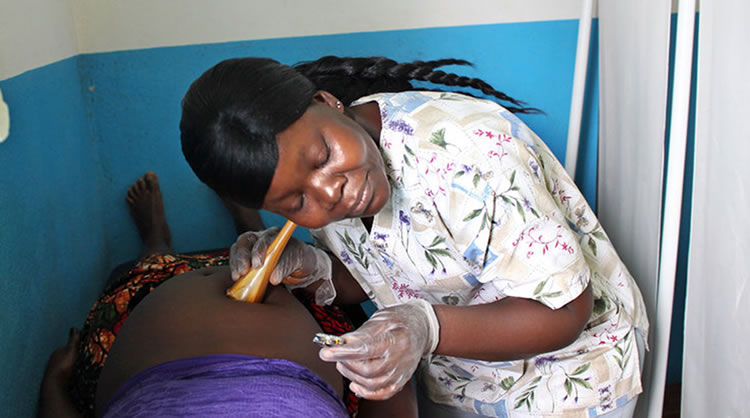
The MTN Group Foundation and the Gates Foundation have launched an artificial intelligence (AI) initiative in Nigeria to help frontline health workers identify pregnancy and childbirth complications earlier and give women access to maternal health guidance.
The Nigeria Maternal Health Multiplier, according to a press release on Tuesday, aims to reach 500,000 women by 2030, equip 5,000 frontline health workers with digital tools and support 500 health facilities to provide more consistent maternal healthcare.
The initiative will use AI, mobile technology and improved connectivity to support pregnant women, health workers and primary healthcare facilities.
The MTN Group noted that it will receive an initial investment of about $25 million between 2026 and 2030, comprising direct and in-kind contributions from MTN and the Gates Foundation.
According to the statement, the four-year partnership was announced at Semafor’s Next three billion event, on the sidelines of the 81st session of the United Nations General Assembly in New York.
Maternal Health in Nigeria
According to the statement, Nigeria has made progress in reducing maternal deaths over the past decade, but significant challenges remain.
Globally, maternal deaths have fallen by 40 per cent since 2000, but progress has stalled, while the risk of maternal death in sub-Saharan Africa remains about 250 times higher than in Western Europe.
“While Nigeria has made real progress in reducing maternal deaths over the past decade, a large burden remains to be addressed: The country accounts for nearly 30 per cent of all maternal deaths worldwide.”
Many of these deaths are preventable, but with only 59 per cent of women completing four or more antenatal care visits, warning signs often go undetected until it’s too late, it noted.
It added that “both the scale of that challenge and the urgency it represents are why Nigeria was selected as the first market for implementation of the Maternal Health Multiplier.”
How the programme will work
The initiative will combine three main interventions: include AI-enabled, phone-based decision-support tools for pregnant women and frontline health workers, affordable smartphones and mobile data for women, and improved internet connectivity at primary healthcare facilities.
The tools are expected to help health workers identify warning signs earlier and provide timely guidance, while giving pregnant women access to trusted health information throughout pregnancy, childbirth and the postnatal period.
MTN noted that the programme will build on the federal government’s Maternal and Neonatal Mortality Reduction Innovation Initiative (MAMII), which is being implemented under the Ministry of Health and Social Welfare’s Sector-Wide Approach.
The Coordinating Minister of Health and Social Welfare, Muhammad Pate, said the partnership would support existing health system reforms.
“Partnerships that work with our existing health systems, rather than around them, are exactly what’s needed to reach mothers who are still falling through the cracks,” Mr Pate was quoted to have said.
READ ALSO: SPECIAL REPORT: Shut clinic deepens healthcare crisis in Benue IDP camp
The Minister of Communications, Innovation and Digital Economy, Bosun Tijani, said the initiative reflects the type of collaboration needed to apply digital transformation to public services.
“For too long, the biggest barrier to improving service delivery in Nigeria, whether in health, agriculture, or education, has not been a lack of innovations, but a lack of focus on the foundational systems necessary to drive adoption,” Mr Tijani said.
Beyond technology
MTN Group President and Chief Executive Officer, Ralph Mupita, said the programme would seek to put locally relevant health information directly in the hands of women and health professionals.
“As artificial intelligence evolves, we can put trusted, locally relevant health insights directly into the hands of mothers and healthcare professionals, tailored to their unique needs and languages,” Mr Mupita said.
Gates Foundation Chief Executive Officer, Mark Suzman, however, stressed that the benefits of AI would depend on reaching people who might otherwise be excluded from such technology.
“AI has enormous potential to improve health, but only if its benefits reach the people who stand to gain the most,” Mr Suzman said.
Discover more from Premium Times Nigeria
Subscribe to get the latest posts sent to your email.
-

 Featured1 day ago
PLATEAU STATE: IS THERE PEACE, OR ONLY THE ABSENCE OF VIOLENCE?
-
News2 days ago
Plateau Killings: Rotjimwa Yilyok Urges Security Agencies to Intensify Action
-
News1 day ago
Former Archbishop of Canterbury Justin Welby Calls for Peace, Protection of Communities During Plateau Visit
-
Business2 days ago
General Business to Drive 72% of Mutual Benefits Assurance’s Projected ₦96.82bn GWP




