
Health
Kenya confirms ninth Ebola case, says all patients improving


Kenya has confirmed a ninth case of Ebola, with health authorities saying all eight surviving patients are improving.
The latest Kenyan case involves a 24-year-old man who is a close relative of the first patient. He developed symptoms while in quarantine and tested positive on 19 October, according to the Kenyan Ministry of Health.
In a statement published on its X account on Tuesday and signed by Patrick Amoth, the Director-General for Health, the ministry said all nine cases belonged to one known cluster, with no evidence of transmission beyond the group.
Kenya’s first patient was a 40-year-old man who travelled from the Democratic Republic of the Congo (DRC) through Uganda before arriving in Nairobi on 3 October. He died at a Nairobi hospital on 5 October.
Treatment and contact tracing
The ministry said the eight surviving patients were stable and responding well to supportive care. It added that it had received 500 doses of medicine to support treatment for confirmed patients.
Contact tracing has also progressed, with 134 of the 135 identified contacts (99.3 per cent) traced and placed in quarantine.

The ministry said contacts who entered quarantine on 6 October and remain symptom-free would complete their 21-day monitoring period and begin returning home from 25 October.
It added that authorities had distributed protective equipment, diagnostic kits, and sample-collection materials to high-risk counties, and established a dedicated laboratory at Kenyatta National Hospital to support testing and prevent disruption to other hospital laboratory services.
Kenya, it noted, has not imposed restrictions on travel, trade or public gatherings. The cases in Kenya are linked to the ongoing Ebola outbreak in the DRC, where the Bundibugyo virus has caused thousands of infections and deaths.
WHO reported more than 8,700 confirmed cases and more than 4,200 deaths in the DRC as of 6 October, with transmission continuing across dozens of health zones.
Nigeria confirms first case
The Kenyan update comes as Nigeria confronts its own Ebola infection, with the federal government confirming the first case in Abuja on Tuesday.
PREMIUM TIMES reported that the patient was a woman who arrived in Nigeria on an international flight from Uganda. She is receiving treatment in isolation at a private hospital in the Federal Capital Territory.
In a statement signed by the Coordinating Minister of Health and Social Welfare, Muhammad Pate, the federal government said it had begun contact tracing and identified 44 close contacts, including healthcare workers, patients, caregivers, and travel contacts.
The government urged healthcare facilities nationwide to remain vigilant, promptly isolate suspected cases, maintain strict infection prevention measures and report suspected infections to public health authorities.
The development has heightened concerns about cross-border transmission, particularly as the outbreak in East and Central Africa coincides with frequent international travel and movement between countries.
Nigeria’s response includes surveillance, laboratory testing, isolation and contact tracing to identify possible infections and limit further transmission.
Discover more from Premium Times Nigeria
Subscribe to get the latest posts sent to your email.









The 44 people identified as contacts of Nigeria’s confirmed Ebola patient will remain in isolation for at least three weeks.
The Coordinating Minister of Health and Social Welfare, Muhammad Pate, disclosed this Tuesday evening during an NTA interview, shortly after the ministry announced Nigeria’s first confirmed Ebola case in the Federal Capital Territory (FCT).
Mr Pate said authorities are currently treating the case as an imported infection and not community transmission.
“At this moment, we are treating it as an imported case, not community transmission,” he said, adding that the situation could change if the virus begins to spread beyond the known contacts.
He said the 44 contacts, including healthcare workers, patients, caregivers and travel contacts, are being isolated at a designated facility in Abuja. At the same time, public health teams determine who may have been infected.
“They remain in communication with their families by phone and other ways, but not physical contact, until we clarify who is infected and who is not,” he said.
Travel manifest obtained
The minister said Nigeria had been conducting risk-based surveillance at points of entry for the past five months through the Nigeria Centre for Disease Control and Prevention (NCDC) and Port Health Services.
He said the aviation industry had also been an important partner in the surveillance effort.
According to Mr Pate, authorities obtained the infected passenger’s travel manifest, which is helping them identify people who may have been exposed.
He said the patient was asymptomatic when she entered Nigeria and developed symptoms after arriving in the country.
“This makes it less likely that the travel itself exposed folks at risk,” Mr Pate said, while noting that authorities were still investigating the circumstances surrounding her entry into Nigeria.
The patient, an unidentified woman who recently arrived in Nigeria on an international flight from Uganda, is currently in isolation and receiving medical care at a private hospital in the FCT.
Symptoms
Mr Pate urged Nigerians and health workers to watch for symptoms including fever, headache, nausea, vomiting, body aches, and severe muscle pain.
He said the Ebola variant involved in the current outbreak is different from the Sudan and Zaire variants, adding that bleeding could occur but is less prominent than with some other Ebola variants.
The case comes amid an ongoing regional outbreak of Bundibugyo Ebola virus, which the NCDC has been monitoring since the outbreak was reported in the Democratic Republic of the Congo (DRC).
The minister also stressed the importance of travel history when assessing suspected cases, particularly among people who have recently travelled to eastern Africa.
He said the Abuja patient had no confirmed travel to the DRC, so authorities presumed she was likely infected in Uganda.
READ ALSO: Ebola in Abuja: 10 things Nigerians should know about the deadly virus
“We presume it is likely that it was picked up in Uganda,” he said, stressing the complexity of tracing the source of infectious diseases.
Regional outbreak continues
The Nigerian case comes amid an ongoing Ebola outbreak in the DRC, where the disease has spread across several provinces.
WHO reported more than 8,700 confirmed cases and more than 4,200 deaths in the DRC as of 6 October, with transmission continuing across dozens of health zones. The outbreak is caused by the Bundibugyo virus.
Kenya reported its first imported case on 6 October: a Kenyan citizen who had been living in the DRC and travelled to Kenya via Uganda.
On 20 October, Kenyan authorities confirmed a ninth case involving a close family member of the first patient.
Uganda, from which the Nigerian patient recently travelled, recorded 20 cases between May and June 2026. The country subsequently ended its outbreak after completing the required 42-day period without a new confirmed case.
Discover more from Premium Times Nigeria
Subscribe to get the latest posts sent to your email.
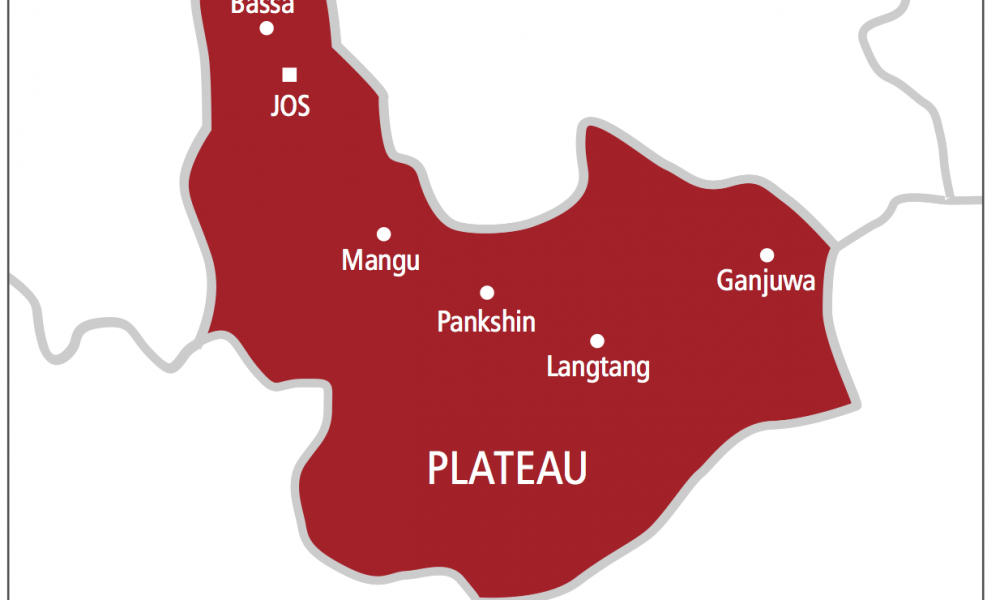
Plateau State has an estimated 11,000 tuberculosis (TB) cases in 2026, with 2,047 patients identified between July and September, according to a state health official.
The cases were disclosed by Yohanna Bot, the monitoring and evaluation officer of the Plateau State Tuberculosis and Leprosy Control Programme, at a media advocacy meeting on community-led monitoring of health services in Jos.
Mr Bot said the estimated burden was based on a TB prevalence rate of 219 cases per 100,000 people, warning that the disease remained a major public health challenge in the state.
“From our quarterly survey, we discovered that between July and September, 2,047 patients were identified and placed on treatment,” he said.
He added that the identified patients were receiving treatment at health facilities across the state.
Tuberculosis is an infectious disease that primarily affects the lungs and spreads through the air when an infected person coughs, sneezes or speaks.
Mr Bot identified malnutrition, advanced age, weakened immunity, overcrowding and HIV infection as factors that could increase the risk of contracting the disease or developing severe illness.
He also expressed concern over stigma and misconceptions surrounding TB, saying some residents attributed the disease to spiritual or ritual causes rather than seeking medical attention.
According to him, such beliefs discourage people from undergoing early diagnosis and starting treatment promptly.
Insecurity, displacement worsen TB risks
Mr Bot said insecurity and displacement were complicating efforts to detect and manage tuberculosis, particularly in Mangu, Jos South and Barkin Ladi local government areas.
He said displacement had led to the establishment of camps for internally displaced persons (IDPs), where overcrowded living conditions could facilitate the spread of the disease.
To address the challenge, he said the state programme was prioritising community outreach and active screening in IDP camps and correctional centres to identify people with TB and link them to treatment.
Mr Bot said patients who received effective treatment could become much less infectious after starting therapy, although the timing depended on their clinical condition and response to treatment.
He, however, raised concerns about shortages of anti-TB medicines, attributing the gaps in availability partly to disruptions in the supply chain and the programme’s dependence on international support, particularly funding from the Global Fund.
He called for increased public awareness to address stigma and misconceptions and urged residents with symptoms suggestive of TB to seek medical evaluation at health facilities.
Community monitoring targets healthcare gaps
Peter Ezekiel, the Plateau State programme officer of the Global Fund AIDS, Tuberculosis and Malaria Integrated Community-Led Monitoring Project, said Nigeria continued to face a significant burden of tuberculosis, HIV and malaria.
He said community-led monitoring was designed to involve residents and other stakeholders in identifying gaps in healthcare delivery and supporting interventions to improve access to essential services.
According to him, the approach helps communities identify barriers such as discrimination, stigma and gender-related challenges while advocating better infrastructure and increased domestic funding for healthcare.
Mr Ezekiel said the initiative had supported infrastructure rehabilitation, service improvements and stronger community participation in Plateau State.
He listed the rehabilitation and re-piping of toilet facilities at the Primary Health Centre in Rantya, Jos South, among the interventions carried out since June.
He said community stakeholders had also donated a scanning machine and 10 iron-framed chairs to the Primary Health Centre in Gangare, Jos North, as well as a blood pressure monitoring device to the facility in Dogon Agogo.
Other interventions included the provision of hospital bed mattresses to the Primary Health Centre in Pushit, Mangu, and tuberculosis sputum collection cups to the COCIN Rehabilitation Centre in Mangu.
Mr Ezekiel said community members had also provided 500 copies of patient enrolment forms to support healthcare delivery.
In Lamingo, he said residents mobilised resources to engage security personnel to protect night-shift workers and property at the local primary healthcare centre, with an agreed monthly payment of N15,000.
He said the interventions had improved infection prevention, patients’ experiences and healthcare delivery.
Mr Ezekiel called for stronger collaboration among communities, government agencies and health partners, alongside adequate funding for primary healthcare and greater accountability in the management of health resources.
READ ALSO: PT Health Watch: What you should know about Tuberculosis, why it persists
He also urged the expansion of national and state health insurance programmes to cover vulnerable people, particularly low-income earners.
Official highlights role of community monitoring
Yakubu Izang, the director of disease control and immunisation at the Plateau State Primary Health Care Board, said community-led monitoring was important for identifying healthcare delivery problems that might otherwise go unnoticed by government agencies.
He said the approach enabled communities and public officials to work together to identify challenges and develop solutions to improve access to healthcare services.
Discover more from Premium Times Nigeria
Subscribe to get the latest posts sent to your email.
-

 News2 days ago
Euromatch NPFL: Matchday 9 results
-
News3 days ago
NUCAP: Nigeria targets 20 million people with 3,700 telecom towers – Technology Times
-
News4 days ago
Gunmen storm Plateau mining site, kill two persons
-
News4 days ago
Nigeria needs stronger collaboration ‘to shape internet governance’ – Technology Times



