
Health
11 African countries record 1,153 mpox cases in six weeks

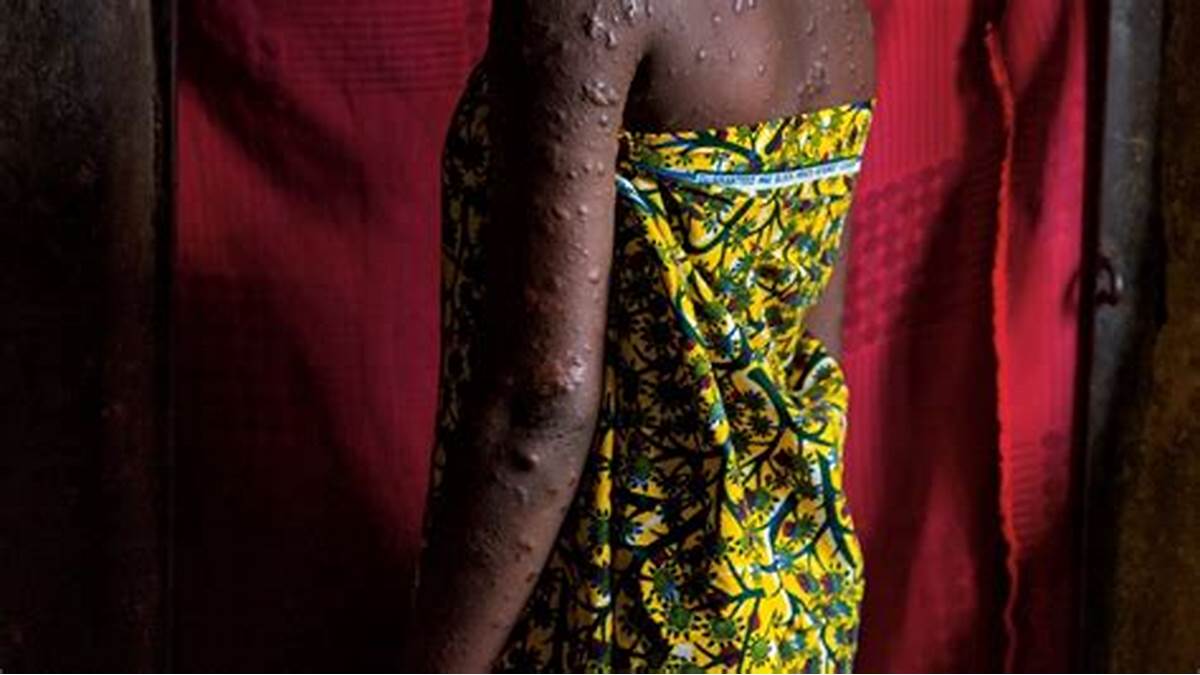

The World Health Organisation (WHO) has reported that 11 African countries recorded active transmission of mpox in the six weeks between 6 July and 16 August 2026, with 1,153 confirmed cases and seven deaths.
The organisation disclosed this in its Mpox: Multi-country External Situation Report published on 14 September.
According to the report, Madagascar recorded 785 cases, the highest during the period, followed by Angola with 184, Kenya with 94, the Democratic Republic of the Congo (DRC) with 41, and Cameroon with 28.
WHO noted that “reported weekly confirmed cases have remained somewhat stable on the continent, with about 200 cases per week in recent weeks.”
However, it cautioned that the figures could be underestimated due to reporting delays and reduced surveillance.

Mpox cases since 2025
The latest figures form part of the multi-country mpox outbreak, which has affected 35 African countries since January 2025.
According to the WHO report, the countries reported 52,424 confirmed mpox cases and 238 deaths between 1 January 2025 and 16 August 2026.
Globally, 65,784 confirmed cases and 264 deaths were reported in 105 countries between 1 January 2025 and 31 July 2026.
The WHO said 32 countries reported 1,370 confirmed cases and seven deaths in July alone, with the African Region accounting for 74.8 per cent of the cases.
New spread
WHO also reported new developments in the virus’s spread. Chile and Hungary reported mpox caused by clade Ib for the first time. In contrast, community transmission of the clade was reported in Czechia, France, Germany, Ireland, Italy, the Netherlands, Portugal, Switzerland and the United Kingdom.
Spain had the highest cumulative number of clade Ib cases in the group, with 241, followed by France with 173, Portugal with 162, and Germany with 140.
Madagascar remains a major concern, with WHO describing its outbreak as the largest mpox outbreak globally and in the African Region since December 2025.
As of 16 August, Madagascar had recorded 3,436 confirmed cases and 22 deaths.
Emergency status
The latest development comes months after the Africa Centres for Disease Control and Prevention (Africa CDC) declared an end to mpox as a Public Health Emergency of Continental Security (PHECS) in January 2026.
READ ALSO: Ebola outbreak spreads to 61 health zones in DRC — WHO
Africa CDC said at the time that the emergency declaration was being lifted as the continent moved from an emergency response towards longer-term control and elimination of the disease.
The agency reported that suspected mpox cases had fallen by 40 per cent and confirmed cases by 60 per cent between early and late 2025, while the suspected case fatality ratio fell from 2.6 per cent to 0.6 per cent.
However, it stressed that mpox remained endemic in some settings and that vaccination would remain central to the response.
The WHO now considers the ongoing multi-country outbreak a graded health emergency and has extended its standing recommendations on mpox until August 2027.
Discover more from Premium Times Nigeria
Subscribe to get the latest posts sent to your email.




A new assessment of 1,480 Primary Healthcare Centres (PHCs) across 16 Nigerian states has found that 97 per cent failed to meet the national minimum staffing requirement, raising fresh concerns about the capacity of the country’s frontline health facilities to provide essential services.
The PHC Operational Capability Report, produced by Orodata Science and Civic Tech, assessed facilities across 277 local government areas in Nigeria’s six geopolitical zones.
The assessment, conducted between October 2023 and June 2025, examined staffing, infrastructure, equipment, electricity, water supply and accessibility using the CheckMyPHC Digital Scorecard.
According to the report, only three per cent of the facilities assessed met the national minimum staffing requirement, while 11 of the 16 states had no assessed PHC that met the standard.
What the staffing standard requires
The national PHC framework recognises adequate staffing as essential to the delivery of quality primary healthcare.
The National Primary Health Care Development Agency’s (NPHCDA) Ward Minimum Health Care Package, developed with the World Health Organisation (WHO), outlines minimum manpower requirements for ward-level PHCs.
For a PHC, the proposed workforce includes a community health officer, public health nurse, three community health extension workers, six junior community health extension workers and four nurse/midwives, with a medical assistant listed as optional.
The same framework recommends that basic essential obstetric care centres be adequately staffed with four midwives or nurse/midwives to provide 24-hour coverage for maternal and newborn care.
Against this staffing framework, the Orodata assessment found that only three per cent of the facilities surveyed met the national minimum requirement.
The report said the shortage was particularly concerning because about 75 per cent of the assessed PHCs were located in rural communities, where such facilities often serve as the first and sometimes only formal source of healthcare for residents.
Staffing gaps, other deficiencies
The staffing problem was not isolated.
The assessment found that many of the facilities struggling to meet staffing requirements were also dealing with inadequate infrastructure and unreliable basic utilities.
According to the report, 40 per cent of the PHCs had broken ceilings or leaking roofs, while 38 per cent operated without electricity.
Water supply was another major concern, with 39 per cent of the facilities relying on unsafe water sources.
Orodata said the deficiencies were interconnected, with poor infrastructure, inadequate staffing, unreliable electricity and water supplies, limited equipment and accessibility barriers often occurring within the same facilities.
The report said the combination could increase risks for patients while placing additional pressure on the health workers available at the facilities.
Newborn care faces major equipment gaps
The assessment also exposed gaps in the capacity of PHCs to respond to complications during childbirth.
It found that 75 per cent of the facilities lacked essential neonatal resuscitation equipment.
Such equipment is required to support emergency interventions for newborns experiencing complications during or immediately after delivery.
The report said the absence of essential newborn-care equipment, alongside staffing shortages and other infrastructure deficiencies, could limit the ability of facilities to provide safe maternal and newborn services.
Accessibility was also a major concern.
According to the assessment, 66 per cent of the PHCs lacked provisions for persons with disabilities and people with mobility challenges.
State-level differences emerge
While the overall findings showed widespread deficiencies, the severity varied across the states assessed.
The report identified Kano and Sokoto as having particularly serious gaps in safe water, reliable electricity and essential newborn-care equipment.
In Gombe, 80 per cent of the assessed PHCs lacked accessibility provisions for persons with disabilities and people with mobility challenges.
The assessment also sought to establish how residents viewed the services provided by their local facilities.
It found that 51 per cent of surveyed community members rated services at their local PHCs as poor.
PHC challenges
The findings are consistent with concerns documented by PREMIUM TIMES in a recent investigation into rural PHCs in Osun State.
The investigation found that despite government investments in the health sector and efforts to revitalise primary healthcare facilities, challenges including inadequate staffing, deteriorating infrastructure, limited equipment and gaps in essential services persisted at some rural facilities.
At one of the facilities visited by PREMIUM TIMES, a single health worker was responsible for attending to pregnant women, children and other patients, while also responding to emergencies outside normal working hours. The facility also lacked a functional laboratory and had inadequate delivery equipment.
The investigation further found that some patients had to travel outside their communities for basic services because the facilities could not provide them.
READ ALSO: Over 30% of solar systems in PHCs fail within three years — Health Minister
Coordinated interventions
Orodata said improving PHCs would require coordinated interventions beyond isolated renovations.
It urged state governments to develop facility-specific plans with clear targets, responsibilities, resources and timelines, alongside regular monitoring.
The organisation also recommended repairs to damaged infrastructure, provision of safe water and reliable electricity, solar or hybrid power systems, recruitment and retention of health workers, and essential neonatal resuscitation equipment for PHCs offering delivery services.
The assessment involved facility visits, direct observation, interviews with health workers and community members, photographs, GPS coordinates and facility records.
Orodata said its CheckMyPHC Digital Scorecard was based on NPHCDA minimum standards and inclusion requirements, and urged authorities to use verified facility-level evidence to guide resource allocation and interventions.
Discover more from Premium Times Nigeria
Subscribe to get the latest posts sent to your email.

The Chairman of the Senate Committee on Health, Ipalibo Banigo, has called for increased investment in Nigeria’s health sector, saying the country remains below its commitments to healthcare financing.
Ms Banigo made the call on Monday in Abuja after she was recognised as the Health Champion 2026 at the Health Sector Reform Coalition (HSRC)/Nigeria Universal Health Coverage (UHC) Civil Society Organisations-Media Mid-Year Review of Nigeria’s Health Sector Reforms.
The event brought together government representatives, civil society organisations, development partners and media professionals to review progress on health-sector reforms and efforts to improve health outcomes in Nigeria.
Increased health investment
Receiving the recognition, Ms Banigo, a medical doctor and senator representing Rivers West Senatorial District, said Nigeria still had significant ground to cover in meeting its health-financing commitments.
She noted that despite the country’s commitment under the Abuja Declaration to allocate 15 per cent of its annual budget to health, actual government spending remains considerably below that benchmark.
“We are not up to the 15 per cent declaration, the Abuja Declaration; we are not there yet. Even at six per cent, we are not close to it,” she said.
She stressed that stronger efforts were needed to increase domestic financing for healthcare.
Her call comes as the National Assembly continues to pursue legislative measures to expand domestic resources available for healthcare.
Legislative
One of the measures sponsored by Ms Banigo is the National Health Act (Amendment) Bill, which seeks to increase the allocation to the Basic Health Care Provision Fund (BHCPF) from one per cent to two per cent of the Consolidated Revenue Fund.
The BHCPF is intended to support the delivery of basic healthcare services, particularly through primary healthcare facilities.
Beyond the BHCPF, Ms Banigo has also sponsored the Sugar-Sweetened Beverages (SSB) Tax Bill, which seeks to replace the existing flat-rate levy on sugary drinks with a percentage-based levy linked to retail prices.
The Senate passed the bill in June 2026.
Under the proposed framework, revenue generated from the levy would support health promotion, disease prevention and primary healthcare.
Health advocacy
The Health Champion 2026 recognition was presented to Ms Banigo for her advocacy and legislative contributions to Nigeria’s health sector.
Presenting the plaque, the Coordinating Minister of Health and Social Welfare, Muhammad Pate, applauded her contributions and encouraged her to sustain the effort.
Mr Pate’s commendation came as stakeholders at the event reviewed ongoing reforms to improve health financing and health outcomes across the country.
READ ALSO: Tax reforms, economic growth critical to Nigeria’s health financing – Official
Ms Banigo expressed appreciation to the organisers, government representatives, civil society organisations, development partners, media professionals and other stakeholders involved in the review.
Ms Banigo said the recognition had further strengthened her resolve to continue supporting policies and reforms aimed at improving healthcare delivery in Nigeria.
Discover more from Premium Times Nigeria
Subscribe to get the latest posts sent to your email.
-

 Business3 days ago
FG settles severance benefits for 2,100 former Nigeria Airways workers after two decades
-
News3 days ago
Revolut confirms customer data breach through fake government requests
-
Health3 days ago
PT Health Watch: How laboratory tests can help detect colorectal cancer early
-
News4 days ago
Mecka AI nears $500M valuation in Sequoia-led deal amid rush for robot training data







